

Internal pouch care Q&A
14th Oct 2026
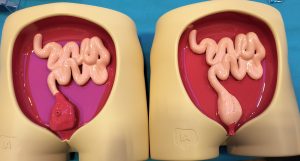
Internal pouch surgery is performed for some people with bowel disease such as ulcerative colitis. The procedure removes all of the colon and rectum and creates a reservoir (internal pouch) from the remaining small bowel which is connected to the top of the anus. The internal pouch acts as a substitute to the rectum, allowing bowel contents to be held internally prior to defecation. For some patients, pouch surgery proves an acceptable alternative to a permanent ileostomy, restoring the function of going to the toilet the traditional way.
Clinical Nurse Specialist Pouch Care, Lisa Allison, answers some frequently asked internal pouch questions.
Q. My new pouch doesn’t seem to be settling well. Is it normal to feel regret after pouch surgery, and what can I do to support my emotional and physical recovery?
It is very normal for it to take a number of months (on the odd occasion up to two years) for pouch function to settle following reversal of the ileostomy. You are essentially having to start from the beginning with learning to read the signals for when you need to pass wind, when it is stool, and building up how long you hold on for (urge resistance) before going to the toilet.
You then need to master what the pouch being properly empty feels like and use a trial-and-error process to work out what you can and can’t tolerate diet wise. Pouch function tends to respond well to a routine and this all takes time (and patience!) and you need to be kind to yourself.
The only reason for having an ileoanal pouch is to improve quality of life over having an ileostomy, and you will have taken time over your decision making. It is very normal to have ‘good’ days and ‘bad’ days, particularly in the first few months. Try and do some form of exercise daily as this not only helps with your strength but your mental health and resilience too. Arrange to spend time with friends and family and talk to them about how you are feeling. If you are happy to, talk to other people who are also learning to get used to having an internal pouch and share ‘tips and tricks’ – everyone is in it together. Many GP surgery websites now have access to local ‘talking therapy’ services that you can self-refer to for more help and support with how you are feeling.
IA offers its own mental health support services: One2One Support and Support Through Therapy – you can discover more about both at iasupport.org/lets-talk.
Always feel free to seek medical advice from your pouch or stoma nurse, the consultant/team who did the surgery, or your GP if you are concerned that your pouch function really is not settling.
Q. Is high pouch frequency something to worry about, and is there a non-surgical way to improve a poor-functioning pouch for issues like occasional leaks?
If a high pouch frequency (the average is four to six in 24 hours) is not normal for you and it does not improve over a few days with changes in diet or adding in Loperamide, we would recommend seeking medical advice. If you know why you might have a higher frequency than normal (e.g., you have eaten a lot of fibre or a spicy curry!) then it should settle down again.
Losing large volumes of liquid stool can lead to dehydration so it is really important to replace salts and electrolytes. It is recommended that all those with an ileostomy or a pouch have a maximum of 1.5 to two litres of hypotonic fluids (tea, coffee, water, squash, etc.) over 24 hours and add in a teaspoon of salt to the diet to replace losses. If you feel dehydrated after having this, you might need St Mark’s solution/electrolyte mix or double strength Dioralyte, but advice should be sought first.

Approximately 20 per cent of people with a pouch will experience leakage at some point. The best thing to try first is adding in a low dose of Loperamide (2mg initially and add in another 2mg if needed) to help slow down the bowel function and thicken the stool, to help prevent leakage.
If the leakage is happening overnight, take a dose before bedtime. If it continues, an examination of the bottom end (specifically the join between the rectal cuff and bottom of the pouch) can help establish if scar tissue has developed at the join and is therefore contributing to the leakage.
Q. Will I have to peel fruit and vegetables forever? Is a pouch-friendly diet a case of trial and error or are there definite no-nos?
Pouch function varies hugely from person to person as well as what diet can be managed with a pouch. What you can tolerate at six weeks after reversal of the ileostomy will be very different to what you feel quite comfortable with four to six months down the line.

Many people are able to eat a varied diet with lots of fruit and vegetables (not necessarily well cooked or peeled) but there is commonly a trade off, i.e., they will more than likely need to go to the toilet more often or will have more wind. Other people have to restrict their diet quite significantly i.e., stick more to protein and carbohydrate-rich foods. It is always very difficult to predict as to how things might be.
Q. Will the pouch restrict any hobbies/activities I may want to do?
Technically, having a pouch should not restrict you from doing any activities you enjoy but it may take a bit more planning, depending on how your pouch function is overall. Some people find that they need to empty their pouch less if they do not eat, or reduce their intake of food before an activity, whereas others will find that eating will slow the function down and leave them better prepared.
There are many people with pouches living their best life and doing yoga, Pilates, swimming, rock climbing and ultra marathon running without too much trouble. It is certainly easier to manage activities if you have a good routine and baseline with the pouch – managing prevention of dehydration is often the key.
Q. Is there any new advice about managing pouchitis?
The key thing with pouchitis (inflammation of the pouch) is being sure that it is the cause of symptoms. The most common symptoms are looser stool than normal (and not responding to changes in diet or addition of Loperamide), increased pouch frequency, abdominal cramping pain, generally feeling under the weather and possibly having other aches and pains, with symptoms getting worse and not better.

Depending on someone’s history and availability, a pouchoscopy would be recommended to check inside the pouch for inflammation and to take biopsies (small bits of tissue from the lining of the pouch) to check for inflammation. A 14-day course of Ciprofloxacin or Metronidazole remains the most common treatment for true pouchitis.
If the episodes of pouchitis are becoming more frequent or if there is little or no response to antibiotics, there is now a lower threshold for starting biologics/advanced therapies which are given as infusions or injections to help dampen down the inflammation in the pouch – usually Vedolizumab, Infliximab (depending on history) or sometimes Ustekinumab. We still don’t truly understand the cause of pouchitis.
Find out more about living with an internal pouch and a host of related information here. You can also explore our internal pouch video presentations.



